

Key Takeaways
- ✓A referral is not finished when it is sent. It is finished when the patient was seen and the report is back in the chart.
- ✓One shared queue with a named owner and a status for every referral beats fax trays, sticky notes, and individual inboxes.
- ✓Five steps close the loop: send complete information, confirm receipt, book the visit, confirm the visit happened, and file the report.
- ✓HIPAA permits sharing patient information for treatment without a separate authorization, but send only what the receiving clinician needs, and check the extra rules for substance use disorder records.
- ✓Track three numbers monthly: how long referrals sit before booking, how many end in a kept visit, and how many close with a report back. CMS measures the last one as MIPS Quality ID #374.
Referral management is the work of making sure a referral your clinic sends actually ends in care. A patient is referred, the specialist sees them, and the report comes back to you. When any step in that chain has no owner and no deadline, the referral drifts. The patient waits, and your chart has no answer when the patient calls to ask what happens next.
This guide covers the loop from start to finish: what counts as a closed referral, where referrals usually break down, how one shared queue fixes most of it, the privacy rules for sharing records, and three numbers worth tracking every month. The examples are illustrative. Nothing here is legal advice, so check your own policies and your state rules before changing how you share records.
What Referral Management Actually Means
A referral is a request from one clinician to another for the evaluation, treatment, or shared care of a patient. Referral management means tracking that request from the day it is made until the report returns and the referring clinician has acted on it. The Agency for Healthcare Research and Quality describes care coordination as deliberately organizing patient care activities and sharing information among everyone involved, and a referral is one of the clearest examples of that work. Read the AHRQ definition in its care coordination guidance.
Do not confuse managing referrals with earning them. Earning referrals is marketing: giving patients and other clinicians good reasons to send people your way. Managing referrals is operations: finishing the work once a referral exists. Our guide to referral marketing for clinics covers the earning side, while this guide stays on the finishing side.
Referrals run in two directions, and both need the same discipline. Outgoing referrals are the ones your clinicians send to specialists, imaging centres, and labs. Incoming referrals are the ones other clinics send to you. A clinic that tracks only one direction will still lose patients, because the same failure, a request with no owner and no follow-up date, causes the loss in both directions.
Where Referrals Break Down
Most clinics do not have a referral problem in one place. They have a small leak at every step, and the leaks add up. The table below shows the five places a referral most often stalls, and what each stall costs you.
| Stage | What goes wrong | What it costs the clinic |
|---|---|---|
| Referral sent | The packet is incomplete: no reason, no recent results, no insurance details | The specialist's office calls back, or the referral sits untouched |
| Receipt | Nobody confirms the specialist received it | The referral is assumed sent and never checked again |
| Booking | The patient is told to call the specialist, and never does | The visit never happens and nobody notices |
| Visit | The patient attends, but your clinic is not told | The chart stays open and the follow-up never happens |
| Report | The report arrives by fax and sits in a pile, or never arrives | The referring clinician cannot act on the result |
The booking stage deserves a closer look, because it is where the most referrals quietly die. Handing a patient a phone number and wishing them well is not a booking. Patients get busy, lose the paper, or put off a call about a problem that frightens them. A referral that depends entirely on the patient making the call will lose a share of those patients every week, and your clinic will not know which ones.
Fixing one step helps, but a single fix does not hold the chain together. A complete packet still fails if nobody confirms receipt, and a confirmed receipt still fails if the patient never books. That is why the queue in the next section matters more than any single improvement. It is the one place where every referral, at every stage, is visible.
One Queue for Every Referral

A referral you cannot see is a referral you cannot manage. Sticky notes, fax trays, inbox threads, and individual spreadsheets all hide open items. Use one shared tracker. Give every referral a status such as Sent, Received, Scheduled, Seen, Report received, and Closed, and assign one named owner to each open item.
Each entry in the queue needs the same small set of facts: the patient, the receiving clinician and practice, the reason, the urgency the clinician set, the date sent, the current status, the owner, and the date of the next action. If any of those fields is blank, the referral is not really being managed.
The queue starts at intake, not after the visit. When the clinician decides to refer, the referral should enter the queue before the patient leaves the building, with the reason and the urgency recorded while they are fresh. That is one more reason to keep your intake flow tight: the facts collected at the front desk are the same facts the specialist's office will ask for.
A shared log only works if it is the only list. The moment a second list appears, a referral can live in one list and not the other, and nobody knows which list is true. Pick one tracker, retire the others, and make the queue part of the daily routine rather than a Friday chore. A simple log that is checked every day beats a fancy system that nobody opens.
One warning about simple logs. A spreadsheet that holds patient names, dates of birth, and clinical details is patient information, and it must sit inside a system covered by your privacy and security rules, with access limited to staff who need it. A personal account or a shared drive with open access does not meet that bar. If your only workable tracker cannot meet it, move the queue into your EHR or a proper referral tool.
The Five Steps That Close the Loop
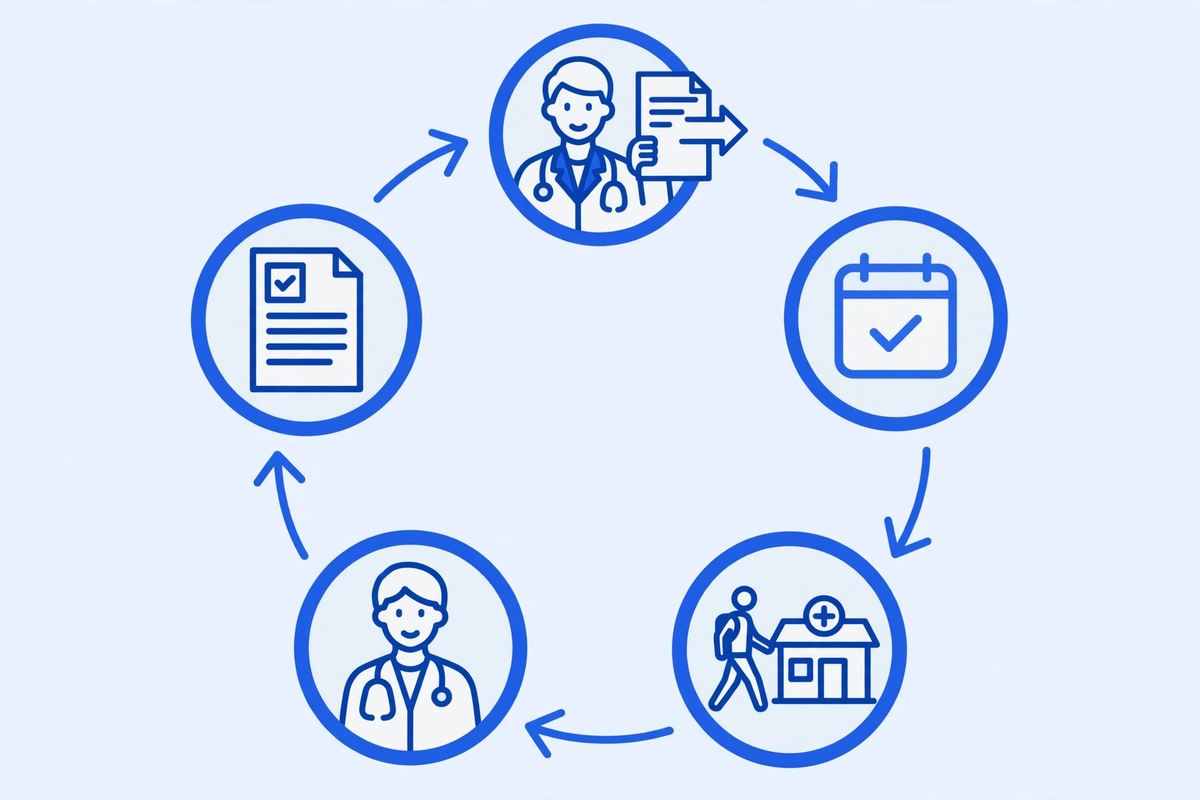
Sending a referral is not the finish line. The loop closes only when your office confirms the patient was seen and the specialist's report is in the chart. Five steps get you there, and each one needs an owner and a date.
- Send complete information. The reason for the referral, the relevant history, recent results, insurance details, and your contact details. An incomplete packet is the most common reason a referral bounces back.
- Confirm receipt within two business days. A short call or message to the specialist's office that asks one question: did you receive it, and is anything missing?
- Book the visit, and help the patient book it. Offer real appointment times where you can, or call the specialist's office with the patient still in front of you.
- Confirm the visit happened. Check with the patient or the specialist's office after the appointment date, and record the outcome in the queue.
- File the report and tell the patient what happens next. The referring clinician reads it, acts on it, and the patient hears the result from your clinic, not from silence.
Set your own deadlines for each step and write them down. As an example, many clinics aim to confirm receipt within two business days, have the visit booked within a week for routine referrals, and request the report within a few days of the visit date. Urgent referrals move faster, and the urgency the clinician sets should decide the clock. What matters is that a timeline exists.
Some referrals need a prior authorization before the specialist will book, which adds a step before the loop even starts. Build the authorization check into step one rather than discovering it after the referral is sent. Our guide to prior authorization for clinics covers how to run that check without it becoming a second queue of its own.
When a patient declines the referral, cannot be reached, or chooses a different specialist, record that, tell the referring clinician, and close the referral as declined rather than leaving it open. An honestly closed referral is useful information.
Incoming Referrals Deserve the Same System
When another clinic refers a patient to you, the same queue applies in reverse. Acknowledge receipt quickly, offer real appointment times, and send the report back promptly after the visit. Referring clinicians remember which clinics reply fast and report back, and that memory shapes where the next referral goes.
Set a first-contact clock for incoming referrals. Same business day is a good target where volume allows, and next business day is the outer limit worth aiming for. The first contact should confirm you received the referral, offer appointment times, and say what the patient should bring. A referral that arrives by phone is easy to lose, which is the same problem our guide to missed calls in medical practices describes. If the call is not logged in the queue, the referral does not exist.
The report back matters as much as the visit. Send the referring clinician a clear note after the visit: what you found, what you did, and what should happen next. Send it promptly, not in a monthly batch, because the referring clinician is waiting to act on it. A clinic that reports back quickly earns the next referral, and a clinic that does not will find its incoming referrals thinning out without anyone saying why.
What HIPAA Allows You to Share
The privacy question comes up in every referral conversation, so here is the plain position. Under the HIPAA Privacy Rule, a covered entity may use and disclose protected health information for treatment, payment, and health care operations without the patient's written authorization. A referral to another clinician for treatment is the textbook case. The US Department of Health and Human Services explains this in its guidance on disclosures for treatment, payment, and health care operations.
Two habits keep that sharing safe. First, send only what the receiving clinician needs for the referral, not the whole chart by habit. The minimum-necessary rule does not apply to disclosures made for treatment, but restraint is still good practice, and it limits the damage if a fax goes to the wrong number. Second, confirm the destination before you send. A fax number copied from an old letterhead, or an email address typed from memory, is how records end up in the wrong office.
Records from substance use disorder treatment programmes carry extra federal protections under 42 CFR Part 2, and sharing them generally needs the patient's consent in a form that rule accepts. Check the consent rules before you share them.
Any vendor that handles your referral data on your behalf, such as referral software or a fax service, needs a business associate agreement. HHS publishes sample business associate agreement provisions that show what it should cover. If a vendor will not sign one, it is not a vendor for referral work.
Three Numbers That Tell You the Truth
You cannot fix what you are not measuring. Three numbers, counted monthly from your own queue, will tell you more about your referral system than any software dashboard. They need no benchmark against other clinics. Compare each month against your own past months, and watch the direction.
| Measure | What it tells you | How to count it |
|---|---|---|
| Days from referral to booked visit | Whether patients are getting in, or stalling | Date booked minus date sent, for the referrals booked that month |
| Share of referrals ending in a kept visit | Whether referrals turn into care | Kept visits divided by referrals sent, measured over 60 to 90 days |
| Loop closure rate | Whether reports come back | Referrals with a report filed divided by referrals sent, over the same period |
The third number has a formal name in quality reporting. CMS runs MIPS Quality ID #374, Closing the Referral Loop: Receipt of Specialist Report, a high-priority process measure that counts the percentage of patients with referrals for whom the referring clinician receives a report. Only the first referral made between January 1 and October 31 counts, to allow time for the report to come back. The measure is listed in the eCQI Resource Center.
The number most clinics skip is the second one, the share of referrals that end in a kept visit. That gap has a name: referral leakage. It is the share of referred patients who never reach a scheduled appointment, or who go elsewhere for care. Measure it from your own queue over the last 60 to 90 days. A leak concentrated in one destination is a conversation with that practice, or a change of destination. A leak spread everywhere is a problem with your own booking step.
Choosing a Tool Without Overbuying
Clinics have three honest options for running the queue, and the right one depends on volume. A clinic sending a handful of referrals a week can run a disciplined shared log inside its EHR or a properly secured tracker. A clinic sending dozens a day needs a referral module or standalone software, with reminders, status tracking, and reporting on the three numbers above.
Software tracks a bad process faster. It does not fix it. Before you buy, write down your five steps, your deadlines, and your statuses, and run them in a simple log for a month. If the process holds, software will make it faster.
When you do evaluate a tool, ask five questions. Does it show every referral in one queue with a status and an owner? Does it remind the owner when a deadline passes? Does it write the booking and the report back into the EHR, or does someone retype them? Will the vendor sign a business associate agreement? And can it report the three numbers without a spreadsheet export?
If the manual chasing is eating hours every week, that is the point where automation earns its place. Healthcare automation can take the routine chasing, the reminders, and the status updates, and leave your team the judgement calls. A patient portal can help too, by showing the patient the status of their referral without another phone call.
A Weekly Routine That Keeps the Queue Clean

A queue that nobody reviews goes stale in a fortnight. Thirty minutes a week, with the queue owner and one clinician, is enough to keep it honest. Run the same five checks every week, in the same order.
- Open referrals past their deadline, oldest first, with a named next action for each one.
- Referrals sent but not yet confirmed received, and the call or message that will confirm them.
- Visits that happened with no report yet, and the request that will chase the report.
- Patients who could not be reached, and how many attempts have been made before the referral is closed as unreachable.
- Declined and redirected referrals, closed properly with the reason recorded and the referring clinician told.
Once a month, add the three numbers to the same meeting, and look at the trend rather than a single month. A queue that is getting cleaner month by month is a system that works. A queue that keeps growing is a sign that the work is being recorded but not done.
The Bottom Line
A referral is a promise your clinic makes on a patient's behalf. The patient trusts that the specialist will see them and that your clinic will know the result. Every referral that drifts breaks that promise quietly, and the patient rarely complains. They simply stop coming back.
The fix is not complicated, and it is not expensive. One queue, one owner per referral, five steps, three numbers, and thirty minutes a week. Start with the queue, run it for a month, and count the three numbers before and after. If you want help shaping the workflow behind it, see the demos or request a quote.

Written by Chloe Vance
Healthcare Marketing DirectorChloe Vance has led search engine optimization and digital patient acquisition strategies for top pediatric, dental, and multi-specialty clinical chains.
Frequently Asked Questions
Common conversational queries evaluated by our natural language models concerning deployment guidelines.